Deep, throbbing cysts along your jawline and chin before every period are not normal surface pimples. In PCOS, high androgens and insulin spikes command your oil glands to produce thick, sticky sebum deep beneath the skin. Here is how dermatologists treat the root causes.
MD Dermatology · Board Certified
Understanding the difference between teenage surface breakouts and adult PCOS hormonal cysts.
In PCOS, ovaries and adrenal glands release higher levels of male hormones (testosterone and DHEA-S). Receptors on hair follicles along the jawline, chin, and neck are exceptionally sensitive to these hormones, enlarging oil glands and producing thick sebum.
Most women with PCOS experience insulin resistance. When blood sugar rises after high-carb meals, insulin levels spike. High insulin lowers sex hormone-binding globulin (SHBG), leaving more free active testosterone circulating to stimulate skin pores.
Because the blockage happens deep in the dermis, PCOS breakouts form painful, hard lumps under the skin that never come to an easy white head. Harsh surface scrubs only irritate the top layer, leaving behind stubborn dark purple-brown marks (PIH).
When hormonal cysts develop along your jawline, the inflammation sits far deeper than an ordinary whitehead. The enlarged sebaceous gland swells under androgen stimulation, while sticky dead cells seal the follicle canal.
Bacteria thrive in this oxygen-deprived space, producing painful pressure. Squeezing or picking a hormonal cyst simply forces bacteria deeper into surrounding tissue, causing scarring and long-lasting pigmentation.
By combining targeted prescription topicals that penetrate deep with insulin-balancing habits, the inflammation calms and normal cell shedding is restored.
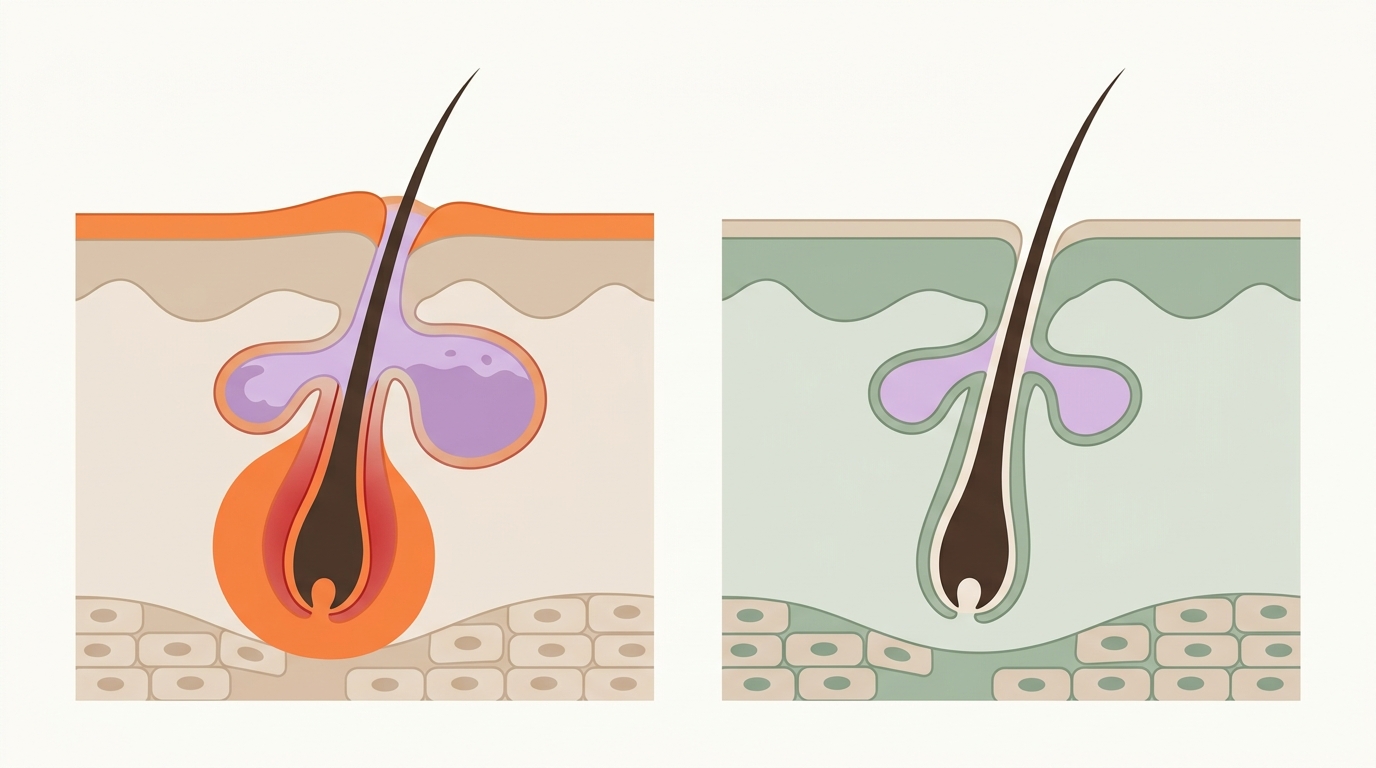
Dermal cross-section: Deep hormonal cyst under androgen influence (left) versus calm, balanced pore after dual-action care (right).

Because PCOS is a metabolic and hormonal condition, dermatologists and gynaecologists often prescribe internal therapies alongside topical skincare.
| Treatment Option | How It Works | Best For | Typical Timeline | Role |
|---|---|---|---|---|
| Spironolactone Oral prescription (50–100mg) |
Blocks androgen receptors in sebaceous glands and reduces skin oil production | Persistent jawline cystic acne in adult women | 8 to 12 weeks for visible reduction | Gold standard oral anti-androgen |
| Combined Oral Contraceptives Anti-androgenic progestins |
Suppresses ovarian androgen synthesis and raises SHBG to bind free testosterone | Irregular cycles paired with hormonal breakouts | 3 to 6 cycles | Hormone regulation |
| Myo-Inositol & D-Chiro-Inositol Nutraceutical (40:1 ratio) |
Improves cellular insulin sensitivity, lowering insulin-driven androgen surges | Insulin-resistant PCOS with sugar cravings | 12 to 16 weeks | Metabolic support |
| Metformin Insulin sensitiser |
Reduces hepatic glucose output and improves peripheral insulin uptake | PCOS with diagnosed insulin resistance or prediabetes | 3 to 6 months | Metabolic correction |
While internal treatments work from the inside, this twice-daily topical regimen prevents pore clogs and clears post-acne marks.
Oil-soluble beta hydroxy acid dissolves trapped surface sebum and smooths the pore entrance without stripping moisture. Lather gently for 60 seconds, then rinse with lukewarm water.
The superstar active for PCOS skin in India. Azelaic acid inhibits 5-alpha reductase (the enzyme converting testosterone to DHT in hair follicles), reduces swelling, and blocks tyrosinase to prevent dark brown PIH marks.
UV radiation worsens hormonal pigmentation and causes trapped sebum to oxidise into blackheads. Apply a lightweight broad-spectrum gel sunscreen every morning before heading out.
Wash away daily pollution and sweat with a mild cleanser. Follow with a lightweight, oil-free moisturiser containing Ceramides or Hyaluronic Acid to keep your skin barrier intact.
A third-generation topical retinoid that binds directly to skin retinoic acid receptors. It normalises rapid cellular shedding inside the pore canal and prevents new microcomedones from forming.
Because insulin spikes drive androgen production in PCOS, small everyday food swaps make a noticeable difference in breakout frequency.
Balanced Meal
Pairing whole grain rotis with green vegetables (palak, methi, or beans) provides soluble fibre that slows down carbohydrate absorption and prevents glucose spikes.
✓ Lowers Glycaemic Spike
Protein Snack
Crunchy roasted Bengal gram delivers 13 grams of plant protein and prebiotic fibre per bowl, making it a satisfying oil-free alternative to deep-fried pakoras.
✓ 13g Plant Protein
Crunchy Snack
A 30 to 40 gram portion of lightly roasted lotus seeds satisfies evening crunchy cravings without sugar or saturated fats that stimulate sebaceous glands.
✓ Mineral Rich & Low GI
Flour Swap
Swapping refined white maida for unpolished ragi, jowar, or bajra delivers complex carbohydrates, zinc, and magnesium to support steady hormone balance.
✓ High Fibre & Minerals
Clean Beverage
Naturally hydrating drink packed with potassium and bio-active enzymes. The ideal clean alternative to sugar-laden bottled sodas and processed juices.
✓ Zero Added Sugar
Herbal Protocol
Drinking 1 to 2 cups of fresh spearmint or peppermint tea daily provides natural anti-androgenic properties that help calm recurring lower-face flares.
✓ Anti-Androgenic Action
Active Movement
Daily 30-minute brisk walks, jogging, or resistance training turn your muscles into glucose sponges, clearing excess blood sugar without extra insulin spikes.
✓ Boosts Insulin SensitivityWatch how dermatologists diagnose jawline breakouts, explain why hormonal acne recurs, and how to stop the cycle.
💡 Dermatologist breakdown of hormonal cysts along the chin, jawline, and effective clinical solutions
Select the option that best reflects what you notice with your skin and cycle.
Your breakouts are linked to luteal phase hormone shifts. Prioritise morning Azelaic Acid 15% to block 5-alpha reductase and evening Adapalene 0.1% over moisturiser. Consult a gynaecologist or dermatologist to evaluate oral anti-androgens like Spironolactone if topicals alone do not halt new cysts.
High insulin levels stimulate the ovaries to produce excess free testosterone while slowing cell repair. Focus on low-glycaemic Indian meal swaps (millets, pulses, healthy fats), incorporate 30 minutes of strength training or brisk walking daily, and discuss Inositol supplements with your physician.
Melanin-rich Indian skin produces excess pigment following any deep cystic inflammation. Never squeeze or pick jawline bumps. Daily broad-spectrum SPF 50 sunscreen combined with 15% Azelaic Acid will suppress tyrosinase activity and accelerate fading.
MyMirror's free AI skin scan checks your lower face in 30 seconds — analyzing acne depth, inflammation levels, and dark marks.
Start Free AI Skin Scan ✨





